
A German instrument maker sent us a set of drawings last year for a range of dissecting forceps and one small scissors pattern. The note on the drawing cost them a field failure, and it was three words long: passivate after marking. The shop they had been using did the opposite, marking the finished parts with a fibre laser at the end of the route because that is where the marking station sat in their line. Six months in the field later, the marks were the first places to show corrosion, and the reason is not the laser. It is the order the laser sits in.
Surgical instrument machining has more in common with a materials problem than with a cutting problem. The geometry is rarely the hard part. The hard part is that the same part has to hold a cutting edge at 58 HRC, be corrosion resistant in a steam autoclave at 134 °C, be repairable by a hospital workshop, and carry an identification mark that survives all of it. Those four requirements fight each other, and the job of the drawing is to say who wins where.
The Four Stainless Families, and What Each One Is For
Almost every reusable surgical instrument in service is one of four stainless families, and picking the wrong one is a decision you cannot fix at the machine.
| Grade | Family | Typical hardness | What it is used for | Why not something else |
|---|---|---|---|---|
| 420 | Martensitic | 45 to 52 HRC | Scissors, hemostats, tissue forceps, jaw inserts | Cheap and hardenable, holds a usable edge at a moderate cost |
| 440C | Martensitic | 58 to 62 HRC | Micro scissors, biopsy punches, high-wear cutting edges | Higher carbon gives edge retention that 420 cannot reach |
| 17-4 PH | Precipitation hardening | 38 to 44 HRC (H900) | Joints, box locks, stapler components, structural instrument parts | Strength and corrosion resistance without a hardening quench |
| 316L | Austenitic | Not hardenable | Cannulae, trays, non-cutting housings, guides | Best corrosion resistance, but it will not hold an edge |
Hardness for 17-4 PH is meaningless without the ageing condition attached: H900 lands around 38 to 44 HRC, H1025 around 35 to 40, and H1150 around 28 to 33. Put the condition on the drawing, not just the number.
The distinction that buyers get wrong most often is between a cutting instrument and a structural one. A pair of scissors is two hardened blades working against each other, so the blade is a martensitic grade, 420 or 440C. A laparoscopic handle is a mechanism, so it is 17-4 PH or 316L, and hardening it would be pointless. When a drawing specifies 316L for a cutting edge, the part will pass a hardness check and fail in use, and no amount of machining skill changes that.
There is a purchasing standard worth knowing here. ASTM F899 is the specification for wrought stainless steels for surgical instruments, where wrought means rolled or drawn stock and says nothing about how the part is formed. What it sets is chemistry, not hardness: it covers austenitic, martensitic, precipitation hardening and ferritic classes, and leaves hardness and heat treatment to the material standards it references. That matters because a supplier who says "we meet F899" has told you the melt chemistry is right and nothing about whether the instrument will cut. F899 does print typical hardness values in its tables, but it labels them as reference only, and leaves the actual hardness requirements to the material standards it points at. The FDA recognised consensus standards database is public, and it is where you can check whether a standard a supplier cites is recognised for the purpose they are using it for. If you want the wider medical picture, our medical device CNC machining guide and the medical devices industry page are the places to start.
Why the Passivation Order Decides Whether the Mark Survives
This is the single most useful thing on this page, and it is the item the opening example got wrong.
A fibre laser mark works by locally heating the surface, melting or oxidizing a thin layer and changing its chemistry. On stainless steel that means the marked area no longer has the passive chromium oxide film that protects the rest of the part. If marking happens after passivation, the mark is the one unpassivated feature on a finished instrument, and in a hospital sterilizer cycle it becomes the corrosion initiation site. If marking happens before passivation, the acid bath removes the disturbed layer and passivates the mark along with the rest of the part.
The consequence for a buyer is that the process route, not the drawing tolerance, is what protects them, and it has to be written down. Our route for a marked stainless instrument is: machine, deburr, mark, passivate, rinse, dry, inspect, package. The mark goes in before the acid, always. Where a customer's own quality system requires marking at the very end, the only defensible alternative is a local re-passivation step after the mark, and that has to be specified and validated rather than assumed.
The same logic runs through the whole surface chain. Passivation on instruments follows ASTM A967 for stainless parts in general, and ASTM F86 where the part is a surgical implant, and the rinse water quality after the acid matters as much as the acid itself. Chloride residue left in a blind hole is a pitting site with a countdown on it, and NPL publishes the reference practice behind the surface and corrosion measurements that catch it. Our CNC parts finishing guide covers the surface options in more depth, and the cleaning side is set out in our medical device machining cleanliness guide. The regulatory side of the same mark, which devices actually need a code on the part and how a mark is graded, is in our UDI marking guide.

Forged or Machined: A Question About Volume, Not Quality
Instrument makers have argued about this for a century, and the honest answer depends on quantity and on how much of the shape is near net.
Forging gives you a grain flow that follows the shape of the part, which is genuinely better for a slender instrument that sees bending loads, and for a slender instrument that carries bending load it is the only economic route at high volume once a die exists. The die costs money and takes weeks. Machining from bar gives you no tooling cost, a design change that costs nothing but programming, and a lead time measured in days rather than months, and modern five-axis work makes shapes that used to require a forging.
| Route | Best at | Tooling cost | Design change | Realistic quantity band |
|---|---|---|---|---|
| Forged then machined | High volume, slender load-bearing instruments | High, one-off | Expensive, die rework | Thousands and up |
| Machined from bar | Prototypes, small families, low and mid volume | None | A reprogramming job | One to a few thousand |
| Metal injection moulded | Very high volume small parts only | High, one-off | Expensive | Tens of thousands |
Our own position is unromantic. Under about 3,000 pieces a year per pattern, forging usually loses to machining, because the die is a fixed cost spread over a small number and a design iteration mid-program kills the business case. Above that, forging starts to win, and the right move is to forge the blank and machine the functional features on it. What we tell customers is not to pick a favourite, but to model both at their own volume before committing. If you want the mechanics of material removal on these grades, our stainless steel CNC machining guide covers feeds, work hardening and the 316L problem specifically.
The Tolerances That Actually Decide Whether an Instrument Works
Instrument drawings carry a lot of dimensions and only a handful of them decide whether the device functions. These are the ones we look for before quoting.
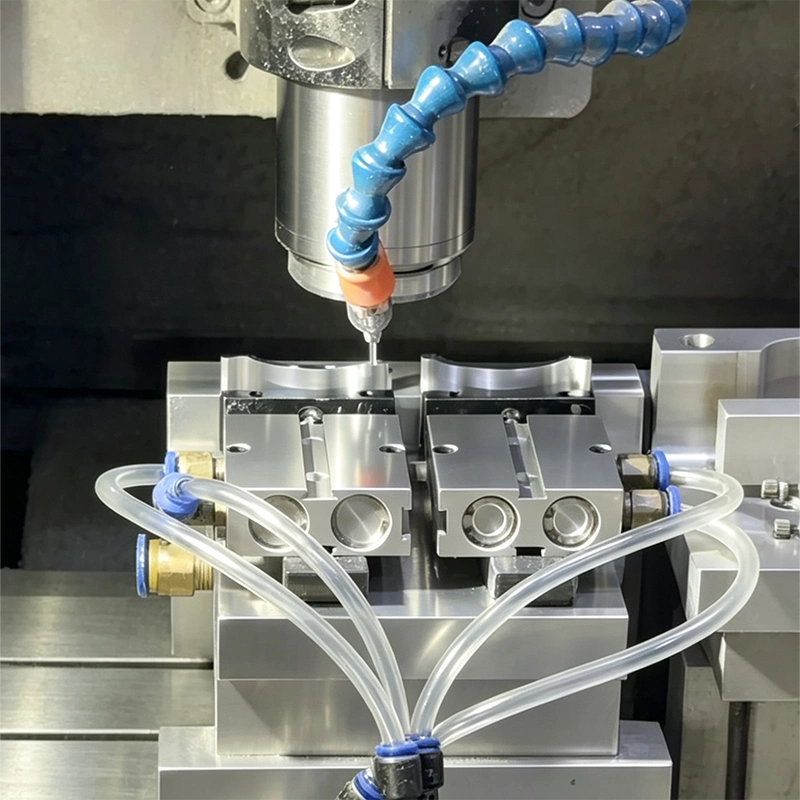
Jaw and blade mating. On a pair of forceps or scissors, the two halves have to mate along their length. A 0.02 mm error in the mating faces turns into a gap at the tip, and a gap at the tip is a surgeon's complaint. We hold ±0.01 mm as standard on these faces and treat the tip alignment as the functional dimension. If your specification needs a first article record to go with it, our first article inspection guide shows what that package contains.
Box lock and pivot fit. The pivot hole diameter and its perpendicularity set how much the instrument rocks. A rock of 0.05 mm at the pivot, on a pivot around 3 mm across, becomes roughly 3 mm at the tip of a 200 mm instrument, which is why the pivot bore is a ±0.005 mm feature on anything longer than about 200 mm.
Ratchet and rack engagement. The teeth that hold a hemostat closed have to engage at every position. This is a form problem rather than a size problem, and it is where a poorly cut rack shows up.
Edge angle on a cutting instrument. The included angle at the cutting edge is set by the application, and grinding it too thin makes a sharp instrument that folds over on first use. On 440C micro scissors the edge is ground after hardening, never before, because hardening distorts a thin edge. What heat treatment does to a machined part before and after the final cut is covered in our heat treated CNC parts guide.
Surface finish on sliding and tissue-contact surfaces. We work to Ra 0.4 to 0.8 µm on tissue-contact and mating surfaces, reached by cutting or by a controlled polish rather than by blasting, because blasting buries debris in the surface it is meant to clean. Our CNC surface roughness guide explains what each Ra band means in practice, and the NIST metrology program is where the traceability chain behind those numbers and behind the hardness values above is defined.

How We Quote an Instrument
An instrument RFQ that goes well has five things on it, and the fifth is the one that saves the most time.
- The grade, and whether the part is a cutting edge or a structure. This decides heat treatment, and heat treatment decides the sequence.
- The functional dimensions, marked as functional. We will hold everything on the drawing, but knowing which three dimensions matter tells us where to spend the inspection time.
- The hardness and where it applies. A whole-part hardness call on an instrument with a hardened blade and a soft handle is a contradiction.
- The marking requirement, including the standard and whether it must survive reprocessing. This is what decides the position of the mark in the route.
- The intended sterilization and reprocessing cycle. This is the one people leave off, and it is the one that tells us whether we are optimising for autoclave corrosion, for repeated handling, or for a single-use device.
If you have those five, you will get a quote within 24 hours, with a plain statement of what we can hold and which step in the route is doing the protecting. If you do not have them yet, send the drawing anyway and our DFM review will flag the ones that look undecided. It is free, and it is much cheaper than finding out at the corrosion test. Send us the drawing.
FAQ: common questions on surgical instrument machining
Which stainless should a surgical scissors blade be?
420 for the majority of general and dressing scissors, in the 45 to 52 HRC range, and 440C when the pattern is a micro or delicate scissors where edge retention at 58 to 62 HRC is the difference between a usable instrument and a returned one. Both are martensitic and both need the edge ground after heat treatment.
Can a surgical instrument be machined instead of forged?
Yes, and under a few thousand pieces a year per pattern it is usually the better route, because there is no die cost and a design change costs programming rather than a new die. Above that volume the economics move to forging the blank and machining the functional features, which keeps the grain flow and the accuracy.
Why does our instrument mark corrode first?
Because the mark disturbed the passive layer and nothing restored it afterwards. Move the marking before the passivation step, so the acid bath passivates the mark along with the rest of the part, or specify and validate a local re-passivation after marking.
What does ASTM F899 actually cover?
The chemistry of wrought stainless steels used for surgical instruments, across austenitic, martensitic, precipitation hardening and ferritic classes. It is a purchasing specification for the material, not a performance specification for the finished instrument, so a certificate against it tells you the alloy is right and nothing about hardness, edge retention or corrosion performance.